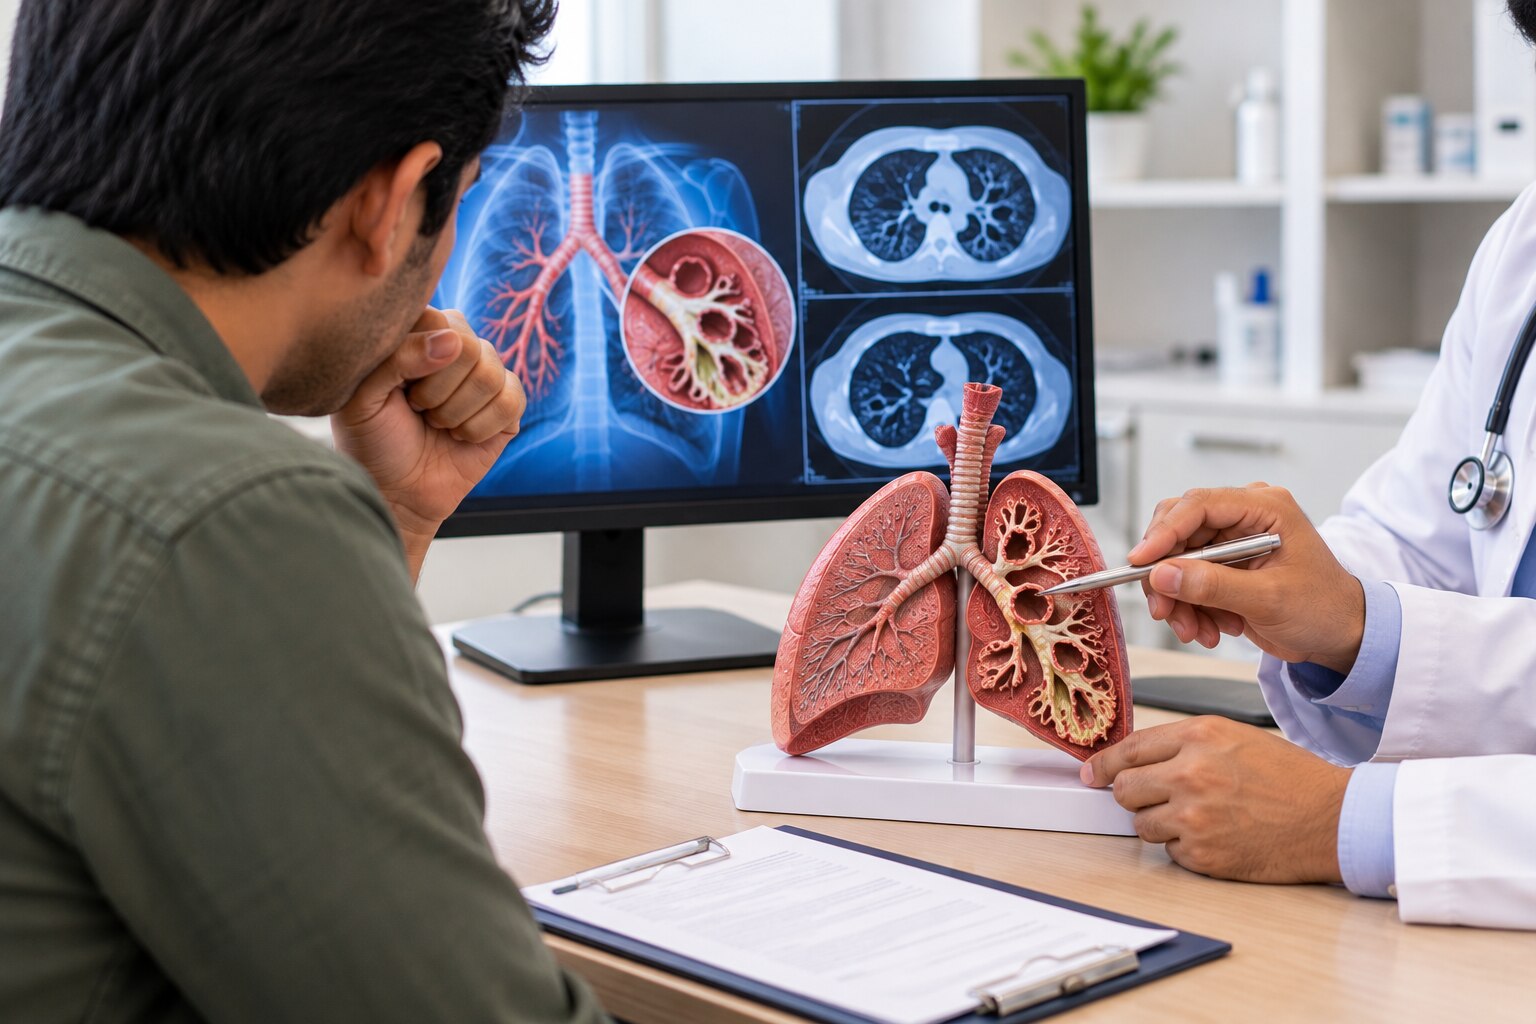
Repeated chest infections, daily phlegm, unexplained breathlessness or an abnormal scan can warrant more than treatment for the next flare-up. By the end, you will know which symptoms and test results justify respiratory referral, how bronchiectasis treatment eligibility is assessed, and what ongoing monitoring involves.
Key takeaways
- Repeated chest infections warrant respiratory assessment.
- Blood in phlegm needs prompt medical evaluation.
- Abnormal imaging or declining lung function supports specialist monitoring.
- Older adults need care adapted to frailty and other conditions.
Which symptoms and test results justify specialist assessment?
The people who should consider bronchiectasis for specialist care include those with repeated treated chest infections, daily or troublesome phlegm, coughing blood, breathlessness or unexplained fatigue. Abnormal chest imaging, declining lung function, or a diagnosis that remains uncertain also justifies respiratory assessment.
| Situation | What it suggests | Action |
|---|---|---|
| One episode of acute bronchitis | A short-term infection that often settles with routine care | Arrange review if symptoms persist or return |
| Three or more treated exacerbations in one year | Frequent bronchiectasis flare-ups | Refer for respiratory specialist assessment |
| Repeated Pseudomonas aeruginosa, hospital admissions, low oxygen levels or rapid deterioration | Higher-risk disease requiring closer monitoring | Seek prompt specialist assessment |
| Severe or ongoing bleeding, acute respiratory distress, blue lips or confusion | A medical emergency | Call emergency services rather than waiting for an appointment |
A single bout of acute bronchitis does not establish bronchiectasis. Suspected bronchiectasis needs follow-up when symptoms recur, sputum remains troublesome, or a scan shows abnormal airways; a chest X-ray alone cannot reliably confirm or exclude it. A thin-section or high-resolution CT is usually the decisive imaging test.
Significant haemoptysis, worsening breathlessness or a rapid change in condition should not wait for routine monitoring. Bring records of treated infections, hospital stays, sputum results and oxygen readings; these details help the respiratory clinician judge urgency and the need for further testing.
How is bronchiectasis treatment eligibility confirmed?
A thin-section or high-resolution chest CT is the key test for confirming permanent airway dilation. A chest X-ray alone cannot reliably establish or exclude bronchiectasis, so a normal X-ray does not end the investigation when symptoms persist.
The clinician interprets the scan alongside your symptom history, number and severity of treated chest infections, lung-function results and examination findings. The same work-up checks whether asthma, COPD, pneumonia, tuberculosis or lung cancer better explains the cough, phlegm or breathlessness.
The assessment may include:
- Blood immunoglobulins to look for antibody deficiency that makes infections recur.
- Testing for allergic bronchopulmonary aspergillosis when asthma, wheezing, high allergy markers or characteristic CT changes suggest it.
- Swallowing, aspiration or reflux assessment when food or stomach contents could be entering the airways.
- Consideration of cystic fibrosis or primary ciliary dyskinesia when bronchiectasis began early, runs in the family or has an unusual distribution.
- Sputum culture and antibiotic sensitivity testing when you produce sputum, especially during a flare, to identify infection and guide treatment.
Bronchiectasis treatment eligibility means receiving an appropriate diagnosis, cause assessment, monitoring plan and airway-clearance or other care suited to your findings. It does not automatically mean long-term antibiotics; those are considered separately for selected people with repeated exacerbations, especially three or more in a year, after reversible factors and sputum results have been reviewed.
Who needs monitoring even when daily symptoms seem mild?
Feeling well between flare-ups does not remove risk. Arrange respiratory monitoring if you have recurrent exacerbations, persistent or repeated Pseudomonas aeruginosa growth, non-tuberculous mycobacteria (NTM), declining spirometry, significant haemoptysis, low oxygen saturation or extensive changes on CT.
1. Send a fresh sputum sample during a productive flare, before antibiotics when possible. Request bacterial culture and antibiotic sensitivity testing so treatment targets the organism. Green, yellow or brown mucus cannot identify the organism or select an antibiotic.
2. Record each treated exacerbation, including the date, antibiotics, emergency visits and hospital admissions. Three or more exacerbations in a year deserve particular attention because prevention may require more than treating each infection separately.
3. Use follow-up to check symptoms and sputum, spirometry, oxygen saturation, airway-clearance technique, nutrition, exercise capacity and vaccination status. Ask for specialist input when NTM is cultured or suspected, or when Pseudomonas keeps returning; do not start preventive macrolides without appropriate NTM testing and medication-safety checks.
A respiratory clinician may repeat spirometry sooner when results fall, oxygen levels drop or breathlessness changes. Significant or ongoing bleeding, severe breathlessness, blue lips or confusion needs urgent assessment rather than routine monitoring. Repeat CT imaging is ordered when the clinical picture calls for it, not automatically at every visit.
What does care involve when infections keep returning?
If treated exacerbations keep returning, bronchiectasis care for frequent infections starts with a structured review rather than an automatic antibiotic prescription. The relevant count is treated bronchiectasis flare-ups, not every cough or positive sputum result.
- Record how many exacerbations needed antibiotics or hospital care, especially whether there were three or more in the past year.
- Send a fresh sputum sample for bacterial culture and antibiotic sensitivity testing, preferably before antibiotics during the next productive flare.
- Check your airway-clearance technique, including whether breathlessness, frailty or limited movement is reducing its effectiveness.
- Update influenza, COVID-19 and pneumococcal vaccinations where appropriate.
- Write an action plan stating which symptoms require a sputum sample, a same-day call or urgent assessment.
A respiratory physiotherapist can teach active cycle of breathing techniques or positive expiratory pressure. They can adapt the method for breathlessness, weak cough, musculoskeletal limitations or reduced mobility. Pulmonary rehabilitation can improve activity tolerance when breathlessness is restricting daily movement.
Long-term preventive antibiotics are considered for selected patients with repeated exacerbations, particularly three or more yearly, after airway clearance, vaccination and other modifiable factors have been addressed. Before a macrolide, clinicians check sputum for non-tuberculous mycobacteria, previous macrolide resistance, an ECG for QT-interval risk, liver tests, interacting medicines and hearing or balance problems.
Treatment needs periodic review.
Inhaled antibiotics may suit selected adults with chronic Pseudomonas infection; they are not ordinary asthma or COPD inhalers and require the correct device and specialist plan.
How should specialist care be adapted for older adults?
Age alone should not exclude an older person from bronchiectasis treatment or specialist review. A bronchiectasis specialist for older adults applies the same disease-severity criteria used for younger adults, then adapts the plan to the person’s safety, function and goals.
| Assessment | What is reviewed | How care may change |
|---|---|---|
| Frailty and function | Mobility, exercise tolerance, nutrition and cough strength | Pulmonary rehabilitation and airway-clearance techniques are adjusted for weakness or breathlessness |
| Treatment safety | Kidney function, hearing, cognition and drug interactions | Antibiotics, macrolides, inhalers and nebulisers are selected and monitored more carefully |
| Airway protection | Swallowing, reflux and aspiration risk | Swallow assessment or aspiration prevention may be needed before intensifying treatment |
The clinician also checks whether the person can use an inhaler, nebuliser or airway-clearance method correctly. A respiratory physiotherapist can adapt active cycle of breathing techniques or positive expiratory pressure for frailty, arthritis or limited mobility.
Monitoring becomes more frequent with chronic Pseudomonas, non-tuberculous mycobacteria, falling lung function, haemoptysis or major heart, kidney or neurological disease. Follow-up can include symptom review, sputum culture when indicated, spirometry, oxygen saturation, nutrition, exercise capacity and vaccination status.
In Pune, Dr Kunjir's Brio Clinic can coordinate respiratory assessment when these decisions involve several risks.
Take these questions to the appointment:
- What caused the bronchiectasis?
- Which symptoms require a same-day call?
- When should sputum be collected?
- Which vaccines, exercises and medicines are appropriate?
Related service
Chest Diseases Treatment BRONCHIECTASIS Bronchiectasis is a long-term condition where the airways of the lungs become widened, leading to a build-up of excess mucus that can make the lungs... |
Frequently asked questions
Which symptoms and test results justify specialist assessment for bronchiectasis?
Seek respiratory assessment for repeated treated chest infections, daily or troublesome phlegm, coughing blood, breathlessness, unexplained fatigue, abnormal chest imaging, declining lung function or an uncertain diagnosis.
How is bronchiectasis treatment eligibility confirmed?
A clinician confirms eligibility by reviewing symptoms and infection history, examining chest imaging such as a CT scan, checking lung function and investigating alternative causes before recommending treatment.
Who needs monitoring when daily bronchiectasis symptoms seem mild?
Arrange monitoring if you have recurrent infections, abnormal imaging, declining lung function, coughing blood, significant breathlessness or other conditions that increase respiratory risk.
What does bronchiectasis care involve when infections keep returning?
Care may include identifying infection triggers, testing sputum, reviewing antibiotics, checking airway-clearance technique, monitoring lung function and creating a plan for flare-ups.
How should bronchiectasis specialist care be adapted for older adults?
A bronchiectasis specialist for older adults should account for frailty, mobility, swallowing problems, memory, hearing, kidney function, medication burden and the ability to perform airway-clearance exercises.
Keywords